

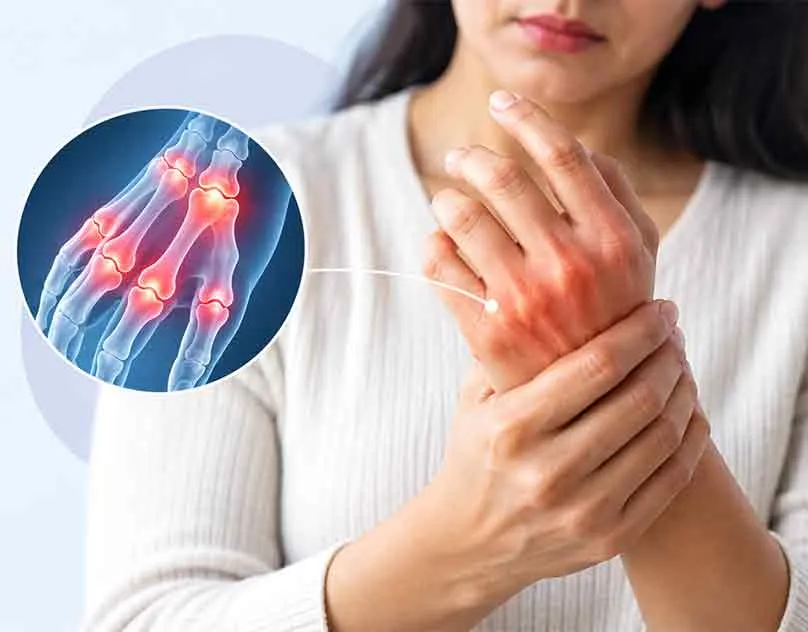
Is Rheumatoid Arthritis Genetic? The Link Between Your DNA and Your Joints
- Is Rheumatoid Arthritis Hereditary or Genetic? There's a Real Difference
- How Genetics Actually Plays Into RA
- Which Genes Are Actually Doing the Damage
- What a Parent or Sibling with RA Really Means for You
- How Common Is RA in India, really?
- The Age Group Most Likely to Brush Off Early Symptoms
- Can You Lower a Risk You Were Born With?
- Where "Reduce Stress, Eat Better" Advice Falls Short
- What a DNA-Led Plan Looks Like Instead
Yes, rheumatoid arthritis (RA) has a genuine genetic link, and one gene region, HLA-DRB1, accounts for a large share of that risk. But carrying the gene doesn’t mean you’ll develop RA. Plenty of people with the same genetic markers never get it, while triggers like smoking, infections, and chronic stress often decide who does.
If joint pain and stiffness have started showing up, especially with a parent or sibling who has RA, it’s natural to wonder how much of this was already written into your DNA. Here’s what the research says
Is Rheumatoid Arthritis Hereditary or Genetic? There's a Real Difference
These two words get used interchangeably, but they aren’t quite the same thing, and the distinction matters for RA specifically.
“Hereditary” usually means a condition is passed down in a direct, predictable pattern, almost like a family heirloom. “Genetic” is broader. It means your DNA plays a role, even if the condition isn’t inherited in a simple, guaranteed way.
RA falls firmly into the second category. It isn’t caused by one faulty gene passed from parent to child the way some hereditary conditions are. It’s shaped by dozens of genes working together with your immune system and your environment. So, while RA does run in families, it isn’t hereditary in the strict sense. It’s genetic, meaning your DNA can raise or lower your odds, without ever guaranteeing the outcome either way.
How Genetics Actually Plays Into RA
RA is an autoimmune disease. For reasons still being studied, the immune system starts attacking the lining of your own joints instead of protecting them. Genetics influences how likely your immune system is to make that mistake in the first place.
Carrying RA-linked genes doesn’t switch the disease on by itself. It sets your immune system’s baseline sensitivity a little higher, so certain triggers, an infection, smoking, prolonged stress, are more likely to set off the chain reaction that leads to RA in someone genetically primed for it than in someone who isn’t.
Which Genes Are Actually Doing the Damage
One region of your DNA stands out well above the rest.
HLA-DRB1 (the “shared epitope”) – this is the single biggest known genetic contributor to RA, responsible for an estimated 30 to 50% of the total genetic risk. It affects how your immune cells recognise and respond to proteins in your body, and specific versions of this gene are strongly tied to the antibody-positive form of RA, the type most linked to joint damage over time.
PTPN22 – involved in regulating immune cell activity. Certain variants make the immune system more prone to overreacting.
PADI4 – linked to a process that changes the shape of certain proteins in a way that can trigger the immune system to attack them.
CTLA-4 – helps keep the immune system in check. Weaker versions of this gene are associated with a higher RA risk.
Here’s something worth knowing research has repeatedly shown that some of these genes don’t act alone. HLA-DRB1 combined with smoking, for example, raises RA risk far more than either factor does on its own. That’s a genetic and lifestyle combination working together, not genetics deciding the outcome by itself.
What a Parent or Sibling with RA Really Means for You
Large twin studies estimate the heritability of RA at roughly 50 to 60%, meaning genetics accounts for a meaningful share of who develops it, while environment and lifestyle account for the rest.
If you have a first-degree relative (parent, sibling, or child) with RA, your own risk is estimated to be 3 to 5 times higher than someone with no family history.
RA affects women about 3 to 5 times more often than men, and often first appears during the most demanding years of a career, typically between the ages of 25 and 55.
A family history is worth taking seriously, especially if you’re a woman in this age range. It doesn’t mean RA is inevitable. It means paying attention to early joint symptoms instead of brushing them off as “just stress” or “just getting older” is genuinely worth doing.
How Common Is RA in India, really?
RA is often assumed to be a Western or older-population disease. Indian data tells a different story.
A large WHO-backed COPCORD survey covering over 56,000 people across India found that roughly 1 in 6 Indians live with some form of arthritis-related pain, with women carrying nearly two-thirds of that burden.
The same survey found that over 1.17 million young women of reproductive age in India are already living with RA, a rate notably higher than global averages.
Community studies put RA prevalence in India between 0.34% and 0.92% of adults, translating to an estimated 5 million or more people living with the condition nationally.
Women make up roughly 80 to 87% of RA patients seen in Indian rheumatology clinics, and the disease frequently starts during peak working and childbearing years.
Because RA often starts quietly, mild stiffness, tiredness, occasional swelling, it’s commonly mistaken for overwork or general fatigue for months, sometimes years, before it’s properly diagnosed.
The Age Group Most Likely to Brush Off Early Symptoms
If you’re managing a demanding job, a household, or both, morning stiffness and joint aches are easy to write off as exhaustion rather than something worth investigating.
A few patterns show up again in women eventually diagnosed with RA:
Chronic, unmanaged stress prolonged stress affects immune regulation and has been linked to earlier onset and more active disease in genetically predisposed people.
Smoking, including secondhand exposure – one of the most well-documented environmental triggers, and it interacts directly with HLA-DRB1 and PTPN22 to raise risk substantially.
Poor sleep – disrupted sleep is associated with higher inflammatory markers, which can influence how early and how severely RA symptoms appear.
Delayed medical attention – many working women postpone seeing a doctor about joint pain for months, often not connecting it to anything serious until stiffness becomes hard to ignore.
Two women with a similar family history and similar day-to-day stress levels can still have very different outcomes, because their genes respond to that stress and those triggers differently. That’s exactly why “manage your stress and eat better” as generic advice doesn’t tell you which specific triggers your body is sensitive to.
Can You Lower a Risk You Were Born With?
To a meaningful degree, yes. RA can’t be prevented with certainty even with a completely clean genetic report, and it can’t be reversed once it develops. But research consistently shows that people with high genetic risk who avoid smoking, manage weight, stay physically active, and get early treatment when symptoms appear tend to have milder disease and better long-term joint outcomes than those who don’t.
In other words, your genes influence the odds. What you do with known triggers, especially smoking, weight, and how quickly you act on early symptoms, still shapes how this plays out for you.
Where "Reduce Stress, Eat Better" Advice Falls Short
Most general advice for people worried about RA sounds the same: reduce stress, eat anti-inflammatory foods, avoid smoking. All true, but not specific.
Two people with a family history of RA can follow identical anti-inflammatory diets and see very different results, because their immune systems don’t respond to the same foods, nutrients, or stress triggers in the same way. Someone with a strong HLA-DRB1 shared epitope may benefit far more from targeted omega-3 and vitamin D support than someone whose risk is driven more by PTPN22-related immune sensitivity. Generic advice can’t tell the difference. A genetic report can.
What a DNA-Led Plan Looks Like Instead
A DNA-informed nutrition and lifestyle plan doesn’t replace your rheumatologist, but it can meaningfully support your treatment and long-term joint health:
If your genes point to a strong HLA-DRB1 or PTPN22 risk, your plan can priorities the specific anti-inflammatory nutrients shown to matter most for that profile.
If your genes suggest higher sensitivity to inflammatory triggers, your plan can flag which foods and habits are more likely to worsen flares for you specifically.
If you’re a smoker or former smoker with high genetic risk, your plan can flag that combination as a priority area, since the two together raise risk far more than alone.
Inside the Report: What You’ll Actually See
In plain terms, a genetic report for RA-related risk can show you:
Your HLA-DRB1, PTPN22, and related gene status
How strongly do your genes interact with smoking and other known triggers
Your genetic tendency toward inflammation
Which nutrients, such as vitamin D or omega-3s, may need more attention for your profile
Lifestyle factors most worth prioritizing based on your specific genetic risk
Why You Only Need to Do This Once
Unlike blood markers such as rheumatoid factors or anti-CCP antibodies, which are checked periodically once symptoms appear, a genetic test only needs to be done once. Your DNA doesn’t change at 30, 45, or 60, so a single test gives you a lifelong reference for risk awareness and prevention planning, well before any symptoms show up.
Know Your Risk Before Your Joints Have to Tell You
Maybe RA runs in your family. Maybe joint stiffness has started, and you’ve been telling yourself it’s just stress or a busy season at work. Either way, knowing your specific genetic risk, and which triggers matter most for your body, gives you a real start most people never get.
A Life code genetic test reads that once. Your risk profile and lifestyle plan are then built around your own report, guided by real health experts throughout.
Take the Life code Genetic Test and Understand Your Rheumatoid Arthritis Risk
One test. One report. Awareness that stays useful for the rest of your life, because your DNA does not change.
FAQ
Frequently Asked Questions
It’s genetic rather than strictly hereditary. RA isn’t passed down through a single gene in a predictable pattern. It’s influenced by many genes, especially HLA-DRB1, working together with environmental triggers like smoking and infections.
Not necessarily. Having a parent with RA raises your risk roughly 3 to 5 times compared to someone with no family history, but most people with a family history never develop RA themselves.
It can’t be prevented with full certainty, but avoiding smoking, maintaining a healthy weight, staying active, and catching symptoms early are all shown to lower risk and improve outcomes in genetically predisposed people.
Diet doesn’t cause or cure RA, but certain nutrients can support the body’s inflammatory response, and how much they help tends to depend on your individual genetic profile.
Piles, also called hemorrhoids, are not considered a purely genetic disease. However, family history may increase a person’s risk, possibly because of inherited differences in connective tissue or vein structure. Other common risk factors include constipation, straining during bowel movements, pregnancy, obesity, and prolonged sitting. A healthcare professional can evaluate persistent bleeding, pain, or swelling.






